
Double Board Certified · Mid-Face Contouring
Cheek Augmentation — structure, projection, definition.
Cheek augmentation improves midface projection or volume through an implant, autologous fat grafting, or carefully selected filler. The correct choice depends on whether the concern is skeletal deficiency, soft-tissue volume loss, tissue descent, asymmetry, or a combination—and whether the patient wants a temporary, biologic, or structural change.
ABFPRS
Facial Plastic & Reconstructive Surgery
ABOto
Otolaryngology — Head & Neck Surgery
AAFPRS
Fellowship Director
In Consultation
"The cheekbone is the architectural anchor of the upper face. When it is well-supported, every other feature looks better."

A Note from Dr. Mourad
"Cheek augmentation restores or enhances mid-face projection — through implants, fat transfer, or carefully-placed injectables. The right choice depends on what the underlying bone provides and how much change is wanted."
— Dr. Moustafa Mourad, MD
Overview
What is cheek augmentation?
Cheek augmentation is a procedure that increases the projection, definition, or volume of the mid-face. It can be performed surgically with a precisely shaped cheek implant placed over the malar bone through small intraoral incisions, or with autologous fat grafting in which the patient's own fat is harvested, processed, and transferred to the cheek.
A cheek concern may involve limited projection, a change in soft-tissue volume, descent, or more than one of these. The consultation first identifies the finding; adding volume is not automatically the answer to every flatter-looking or lower cheek.
Where appropriate, discuss how an implant, a volume-restoring treatment, or a lifting procedure would address different parts of the concern. Each option has limitations and a different recovery and risk discussion. The proposed treatment should be described specifically rather than grouped under a promise of general facial rejuvenation.
Some patients are deciding between adding volume with an implant or filler, reducing lower-cheek fullness with buccal fat surgery, or addressing descent with a lift. Those are different diagnoses, and the examination should decide among them.
Anatomy & planning
Skeletal projection
Limited malar or submalar bony support may be treated with a properly selected implant in appropriate patients.
Anatomy & planning
Soft-tissue volume loss
Fat grafting or filler may restore selected volume, but each has different predictability, reversibility, longevity, and risk.
Anatomy & planning
Tissue descent
A cheek that has moved downward is not always corrected by adding volume. Midface lift or facelift planning may be more appropriate when descent is the primary problem.
Anatomy & planning
Mixed anatomy
Many patients have a combination of bone shape, volume loss, and descent. Adding too much volume to compensate for descent can create heaviness or distortion.
Anatomy & planning
Cheek implant
A structural, non-resorbable option that changes projection and contour. It requires surgery and carries implant-position, infection, palpability, asymmetry, and revision considerations.
Anatomy & planning
Fat grafting
Uses the patient’s own fat to restore volume. Some transferred fat is retained and some is resorbed; contour, survival, and the need for additional treatment vary.
Anatomy & planning
Filler
Offers a temporary or semi-temporary office-based change with no surgical implant, but it can obscure anatomy, migrate, cause vascular complications, or create cumulative heaviness. It should not be presented as a risk-free trial of surgery.
Anatomy & planning
Prior-filler planning
Patients should identify prior filler products, dates, and locations when possible. Hyaluronic-acid filler may sometimes be dissolved before definitive evaluation; other materials may not be reversible. Examination, ultrasound, or staged treatment may be appropriate in selected cases.
An Established Academic Authority
Double board certification. Fellowship director. Published author. A surgeon's surgeon.
ABFPRS
Board Certified
American Board of Facial Plastic & Reconstructive Surgery
ABOto
Board Certified
American Board of Otolaryngology — Head & Neck Surgery
NYMC
Clinical Assistant Professor
Otolaryngology · Clinician Scholar Pathway
AAFPRS
Fellowship Director
American Academy of Facial Plastic and Reconstructive Surgery
Textbook
Published Author
Contributions to the academic literature of facial plastic surgery
Dual board certification in both Facial Plastic & Reconstructive Surgery and Otolaryngology — Head & Neck Surgery.
01 · Why Dr. Mourad
Diagnosis first, then a plan that fits.
Dr. Mourad evaluates the cheek in the context of the whole face — chin, jawline, and orbital rim — never in isolation.
Augmentation options range from precise injectable contouring to permanent implant placement; the recommendation is matched to the goal and the timeline.
Implants are placed through hidden intra-oral incisions with precise sub-periosteal pocket dissection.
02 · Ideal Candidates
Who benefits most from this operation.
Candidacy is determined together at consultation. The most satisfied patients share three things in common.
I
Flat or Receding Mid-Face
Patients with naturally flat zygomatic projection seeking more defined cheek structure.
II
Age-Related Volume Loss
Patients whose mid-face volume has decreased with age, seeking restoration of youthful contour.
III
Comprehensive Facial Balance
Patients pursuing overall facial balance — often paired with chin or jawline refinement.
If this describes you, the next step is a quiet, unhurried conversation — not a sales call.
An Honest Note
When this operation may not be right for you.
Patients seeking dramatic, non-anatomic projection are better served by careful counseling and a more measured plan.
Patients with unrealistic expectations of how a single procedure will transform the whole face benefit from a longer consultation.
Patients with active dental infection or unhealthy oral mucosa should defer until those are addressed.
Smokers and patients on certain medications need a planned optimization window.
03 · Approaches
Three paths to cheek definition.
Cheek augmentation is not a single operation. The right answer depends on whether the change you want is structural, volumetric, or a contour adjustment that should remain reversible.
1 of 3 · Cheek Implant Augmentation
04 · Technique
Implant vs fat transfer.
The two definitive options for lasting cheek augmentation. Each suits a different patient and a different aesthetic goal.
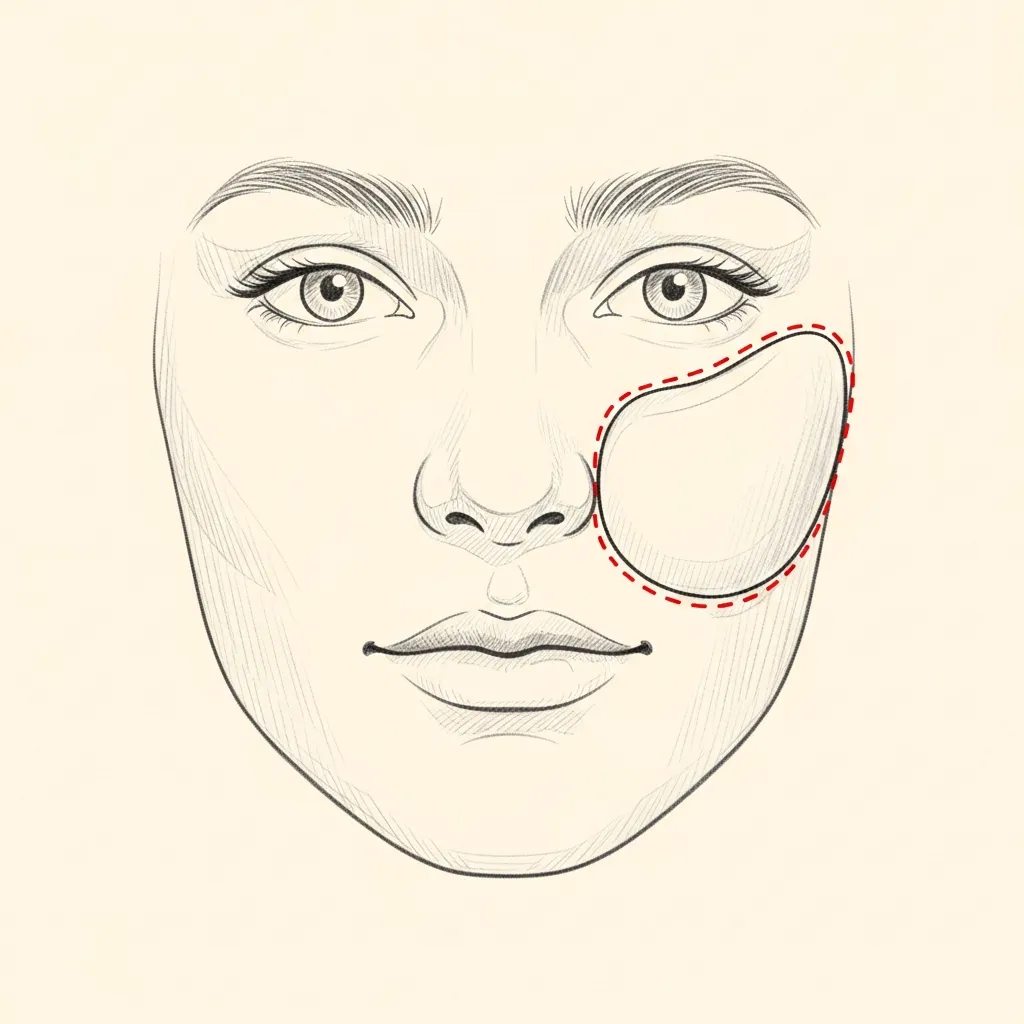
Implant
Permanent structural projection
A silicone implant is placed against the malar bone through a hidden intra-oral incision and secured to maintain stable position. The change is immediate, definitive, and permanent.
Implants are the right choice when the goal is significant projection of a flat or under-developed mid-face — and when the patient wants a single operation with a one-time recovery.
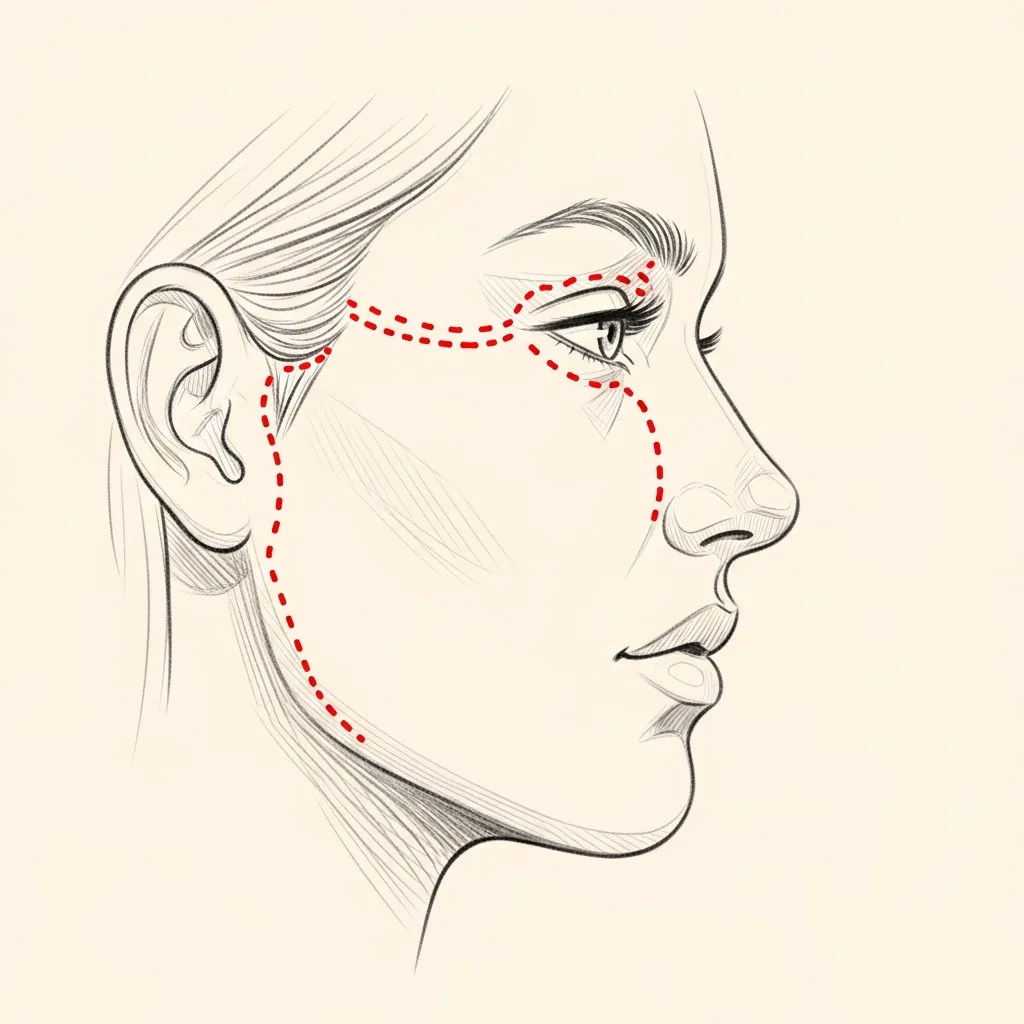
Fat
Soft autologous volume
Fat is harvested from the abdomen or flanks, processed, and re-injected into the mid-face in small aliquots. The result is soft, natural-feeling volume.
Best suited to age-related volume loss and patients who prefer a biologic solution. A portion of grafted fat will not survive, so modest over-correction is planned.
Illustrative diagrams. The right approach is determined together based on starting anatomy and aesthetic goal.
A decision, not a menu
Implant, fat transfer, or filler?
The same word — cheek augmentation — can describe three different interventions.
| Implant | Fat transfer | Filler | |
|---|---|---|---|
| Longevity | Permanent | Largely permanent, partial resorption | 9–24 months |
| Reversibility | Removable | Difficult | Hyaluronidase, if HA |
| Downtime | About 1 week | 3–5 days | None |
| Best for | Skeletal deficiency | Volume loss with good skin | Trial or small refinement |
| Revision | Exchange or removal | Additional grafting | Dissolve and restart |
Begin the conversation
A careful, honest evaluation is the right first step.
Cost & Insurance
How Much Does Cheek Augmentation Cost in NYC?
Cheek implants and other facial implants typically range from $10,000 to $14,000+. Fat transfer and injectable filler are different procedures with different costs and are quoted separately — the implant figure does not apply to them.
Cheek augmentation is a cosmetic procedure and is typically self-pay. After consultation, our office provides a personalized estimate based on the recommended plan. Payment is arranged directly with the practice. Payment terms and any required deposit are reviewed when surgery is scheduled.
| Operation | Typical surgical investment |
|---|---|
| Cheek implants and other facial implants | $10,000–$14,000+ |
What May Affect Cost
- Augmentation technique used
- Whether implants are used
- Whether combined with other procedures
- Type of anesthesia
- Surgical setting
- Postoperative care
The prices listed are provided as general estimates of typical surgical investment and are not guaranteed quotes. Surgical fees vary based on the patient's anatomy, the complexity of the procedure, previous surgery, operative time, anesthesia and facility requirements, implants or hardware, virtual surgical planning when applicable, and whether multiple procedures are performed together. An exact surgical fee is provided following consultation and development of an individualized treatment plan.
06 · Recovery
What healing actually looks like.
Stage 01
First 24 Hours
Initial recovery focuses on rest, hydration, and following all post-operative instructions exactly. Pain is managed with multi-modal non-narcotic protocols where appropriate.
Stage 02
Week 1
Swelling and bruising peak in the first few days and improve steadily through the first week. Most patients are presentable for casual social activity by the end of week two.
Stage 03
Weeks 2 – 4
Through weeks two to four the early result begins to settle. Light cardio resumes around three weeks; vigorous exertion and contact activities are deferred per the operative plan.
Stage 04
Months 1 – 6
The final refined result emerges progressively over the following months as residual swelling continues to resolve. Follow-up visits are scheduled across the first year.
Have a specific question?
Send a brief note describing your anatomy or concerns — the office will route it directly to Dr. Mourad for review.

Before You Arrive
Your consultation, prepared.
Bring photographs relevant to your concern, when available.
Bring records from any prior surgery, when available.
List current medications, supplements, and blood-thinning agents.
Note any prior anesthesia issues or chronic medical conditions.
Allow 60 minutes for the first consultation.
Bring questions; no decisions are made at the first visit.
Frequently Asked
Patient questions, honestly answered.
Augmentation adds projection or volume. A lift repositions descended tissue. The examination determines whether the concern is deficiency, depletion, descent, or a combination.
They are designed as long-term implants but can be removed or revised. Position, tissue response, aging, infection, trauma, or changing preferences may lead to future surgery.
Clinical references
This page draws on published clinical practice guidelines and public-health references. These sources inform general patient education and do not replace an individual evaluation with Dr. Mourad.
- 01Facial implant material systematic review PubMed PMID: 40225117
- 02Facial autologous fat-grafting complications systematic review PubMed PMID: 38260755
The Most Important Step
Your expert consultation.
A careful evaluation by a double board-certified physician is the right first step. The conversation is unhurried, the diagnosis is honest, and the operative plan is built around what your anatomy can sustain and what you actually want.