
Double Board Certified · Functional Nasal Surgery
Deviated Septum in NYC
A deviated septum is one of the most common — and most under-diagnosed — causes of chronic nasal obstruction. The cartilage and bone that divides the nose has moved off the midline, narrowing one or both airways and changing how breathing feels with every breath.
ABFPRS
Facial Plastic & Reconstructive Surgery
ABOto
Otolaryngology — Head & Neck Surgery
AAFPRS
Fellowship Director

In Consultation
"Many patients have lived with one-sided breathing problems for so long that they have stopped noticing them. The diagnosis is often a relief."

A Note from Dr. Mourad
"A deviated septum is one of the most common — and most under-diagnosed — causes of chronic nasal obstruction. The cartilage and bone that divides the nose has moved off the midline, narrowing one or both airways and changing how breathing feels with every breath."
— Dr. Moustafa Mourad, MD
Overview
What is a deviated septum?
A deviated septum is a structural deformity in which the wall of cartilage and bone that divides the two nasal passages is shifted off the midline. Most people have some degree of septal deviation — by many estimates around 80% — and most never notice it. It becomes a problem only when the bend narrows the airway enough to cause symptoms.
Septal deviation can be congenital — present from birth or developed during craniofacial growth — or post-traumatic, following a blow to the nose at any age. The deviation may involve the cartilaginous, bony, or both portions of the septum, and is often accompanied by compensatory enlargement of the inferior turbinate on the opposite side.
Common symptoms include nasal obstruction (often one-sided), recurrent sinus infections, post-nasal drip, snoring and disturbed sleep, recurrent nosebleeds, and difficulty exercising. Diagnosis is made on examination, supplemented by nasal endoscopy and, when relevant, CT imaging.
An Established Academic Authority
Double board certification. Fellowship director. Published author. A surgeon's surgeon.
ABFPRS
Board Certified
American Board of Facial Plastic & Reconstructive Surgery
ABOto
Board Certified
American Board of Otolaryngology — Head & Neck Surgery
AAFPRS
Fellowship Director
American Academy of Facial Plastic and Reconstructive Surgery
Textbook
Published Author
Contributions to the academic literature of facial plastic surgery
Dual board certification in both Facial Plastic & Reconstructive Surgery and Otolaryngology — Head & Neck Surgery.
Castle Connolly Top Doctor — Plastic Surgery, 202602 · Symptoms
How this condition typically presents.
Three patterns are most common. Patients often recognize themselves in one or more of these.
I
One-Sided Obstruction
Difficulty breathing through one side of the nose more than the other, often worse when lying on a particular side at night.
II
Mouth Breathing & Snoring
Mouth breathing on waking, dry mouth, snoring, and sometimes a noticeable reduction in aerobic capacity.
III
Recurring Sinus Issues
Frequent sinus infections, sinus pressure, or chronic congestion that does not respond fully to medical therapy.
03 · Diagnosis
How the diagnosis is made.
Diagnosis begins with a careful history — when symptoms started, what makes them better or worse, and what has been tried.
Examination includes anterior rhinoscopy and, where appropriate, nasal endoscopy with a small flexible scope to visualise the deeper nasal cavity and sinus outflow tracts.
Imaging — typically a focused sinus CT — is obtained when the examination and history warrant it, and is reviewed in detail at the visit.
04 · Treatment Options
Treatments matched to the diagnosis.
Treatment is individual. The right answer ranges from continued medical therapy to a focused minimally-invasive procedure to definitive structural surgery. For treatment options, surgical candidacy, and functional nasal airway planning, visit deviated septum repair in NYC.
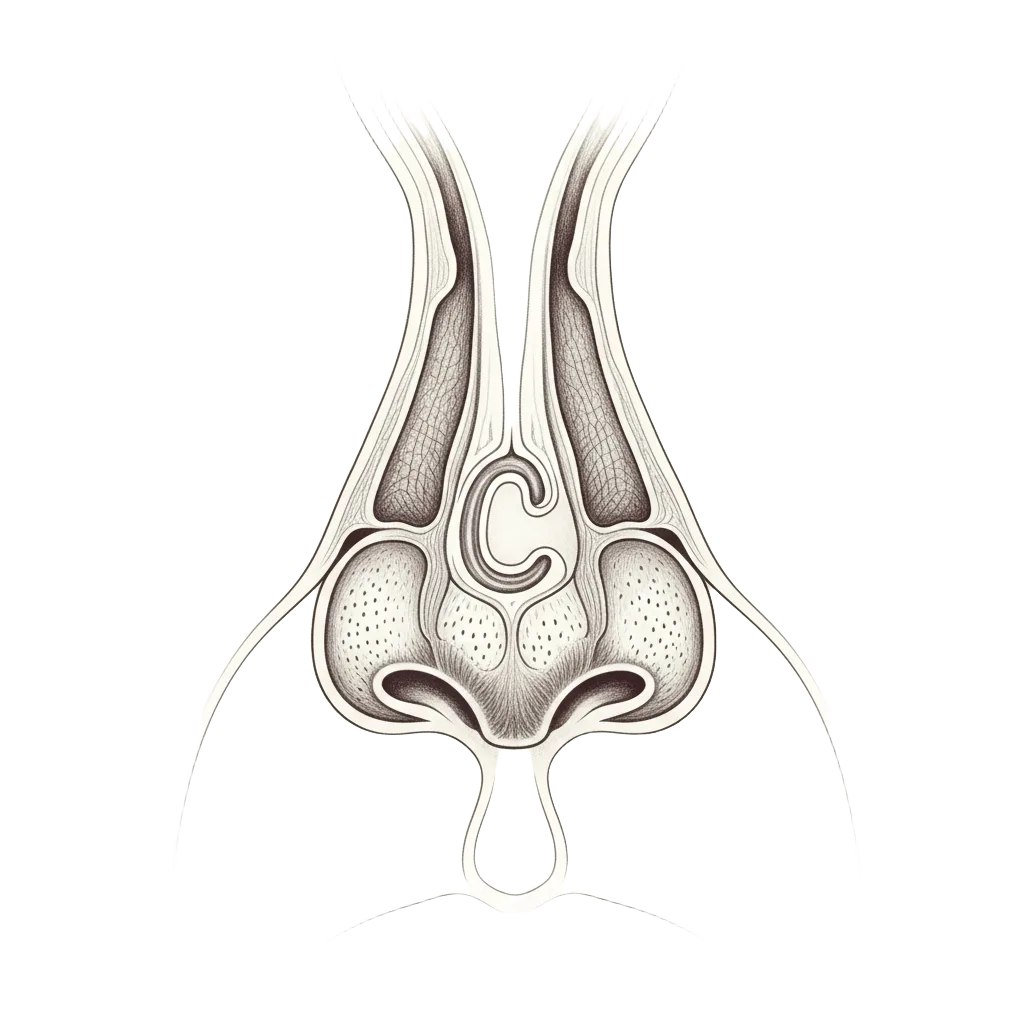
Septoplasty
When the septum is the structural cause of obstruction — deviated septum surgery in NYC. Definitive correction of the deviated cartilage and bone.
Learn More
Septorhinoplasty
When cosmetic refinement is wanted in the same operation.
Learn More
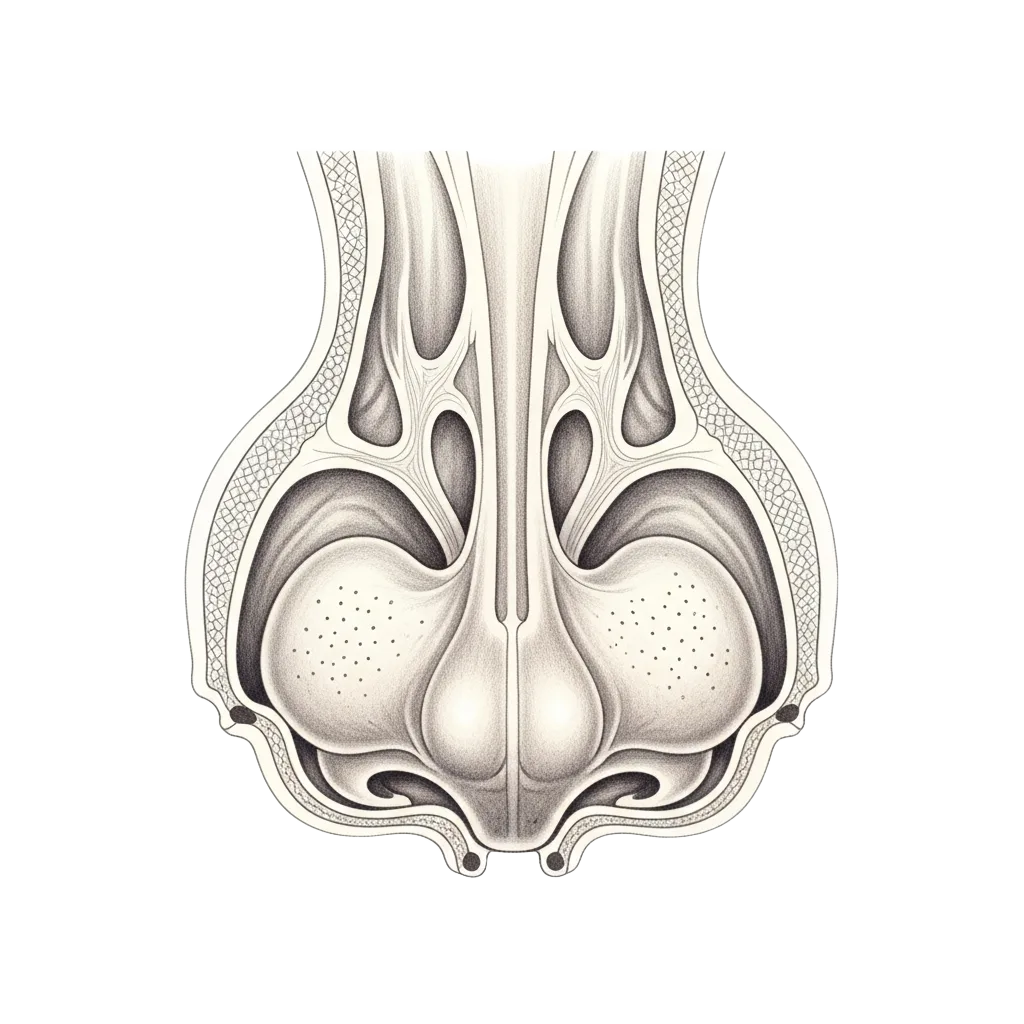
Turbinate Reduction
Often combined with septoplasty when enlarged turbinates contribute to the obstruction.
Learn More
01 · Why Dr. Mourad
Diagnosis first, treatment second.
Dr. Moustafa Mourad is double board-certified in Facial Plastic & Reconstructive Surgery and in Otolaryngology — a combination uniquely suited to evaluating both the structural and the medical components of nasal and sinus disease.
Every evaluation begins with a careful history, examination, and — where indicated — endoscopy and imaging. The diagnosis is made before any treatment plan is discussed.
Medical therapy is exhausted before surgery is recommended. When surgery is the right answer, the operation is the one your anatomy and disease actually require.
When to Seek Care
When to seek care promptly.
Severe facial pain, high fever, or visual changes — these warrant urgent evaluation.
Significant facial swelling or redness around the eye — evaluate immediately.
New or worsening obstruction after a recent injury — evaluate within days.
Persistent symptoms beyond a few weeks despite over-the-counter measures — a careful evaluation is reasonable.
Outlook
What to expect.
When the diagnosis is correct and the right treatment is applied, the outlook is generally good. Many patients describe meaningful improvement in sleep, exercise tolerance, and day-to-day energy.
When symptoms persist despite treatment, the workup is re-opened. Persistent symptoms with no answer almost always mean the diagnosis is incomplete.

Living Well
Day-to-day measures that help.
Daily saline irrigation, control of indoor allergens, and good sleep hygiene meaningfully reduce day-to-day symptoms for most patients.
Medical therapy, when prescribed, works best when used consistently rather than as needed — this is one of the most common reasons treatment seems to fail.
Frequently Asked
Patient questions, honestly answered.
Structural blockage is often reproducible, positional, or persistently worse on one side and does not fully clear with decongestants. Allergic or inflammatory causes typically fluctuate with exposures and often improve with a 4–8 week trial of intranasal corticosteroid therapy. Clinic assessment uses anterior rhinoscopy and nasal endoscopy to inspect the septum, turbinates, and valves; selective objective tests such as allergy testing or acoustic rhinometry may be useful. An in‑person exam is required to separate structural from mucosal contributors and to plan appropriate treatment.
Yes. Initial management for mucosal contributors usually includes daily intranasal corticosteroid sprays for 4–8 weeks plus saline irrigations. Short topical decongestant trials can help identify reversible congestion but are not appropriate long term. If symptoms persist despite adequately directed medical therapy and objective exam findings show anatomic obstruction, surgical options such as septoplasty or turbinate reduction are considered. The decision to refer for surgery is individualized and made after clinical reassessment.
The Most Important Step
Get an expert evaluation.
A careful evaluation by a double board-certified physician is the right first step. The conversation is unhurried, the diagnosis is honest, and treatment is matched to what you actually have.